Compare versions
Version 1 → Version 2 (current). Removed · Added. This shows the entry's text as it is written, including its formatting marks.
Version 1 · Version 2 (current) · Version history
Side by side · Together
Version 1Version 2 (current)
CAR T-cell therapy is a treatment in which a patient's own T cells, a type of white blood cell, are genetically engineered in a laboratory to recognise a chosen target, multiplied, and infused back into the patient, most often to attack cancer cells.
CAR T-cell therapy is a treatment in which a patient's own T cells, a type of white blood cell, are genetically engineered in a laboratory to recognise a chosen target, multiplied, and infused back into the patient, most often to attack cancer cells.
The letters CAR stand for chimeric antigen receptor: an engineered protein placed on the surface of the T cells that, as the U.S. National Cancer Institute (NCI) explains, [helps them bind to antigens on cancer cells](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells) and improves their ability to kill them. An antigen is a molecule, usually a protein, that the immune system can recognise. "Chimeric" refers to the receptor being assembled from parts of different proteins. As of NCI's page updated 26 February 2025, the U.S. Food and Drug Administration (FDA) had approved [seven CAR T-cell therapies](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells), all of them for cancers of the blood. Since 2021 the same approach has also been tested in severe autoimmune diseases.
The letters CAR stand for chimeric antigen receptor: an engineered protein placed on the surface of the T cells that, as the U.S. National Cancer Institute (NCI) explains, [helps them bind to antigens on cancer cells](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells) and improves their ability to kill them. An antigen is a molecule, usually a protein, that the immune system can recognise. "Chimeric" refers to the receptor being assembled from parts of different proteins. As of NCI's page updated 26 February 2025, the U.S. Food and Drug Administration (FDA) had approved [seven CAR T-cell therapies](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells), all of them for cancers of the blood.[1] Since 2021 the same approach has also been tested in severe autoimmune diseases.
3 unchanged paragraphs
## How a CAR works
## How a CAR works
A T cell normally recognises its targets through its own T-cell receptor, which only sees fragments of protein presented by other cells in a particular molecular setting. A CAR replaces that recognition with a binding part borrowed from an antibody, so the cell can be pointed at a surface molecule chosen by the receptor's designers, without that setting being required.
A T cell normally recognises its targets through its own T-cell receptor, which only sees fragments of protein presented by other cells in a particular molecular setting. A CAR replaces that recognition with a binding part borrowed from an antibody, so the cell can be pointed at a surface molecule chosen by the receptor's designers, without that setting being required.
A 2021 review in *Blood Cancer Journal* by Robert C. Sterner and Rosalie M. Sterner describes a CAR as having [four main components](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/):
A 2021 review in *Blood Cancer Journal* by Robert C. Sterner and Rosalie M. Sterner describes a CAR as having [four main components](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/):
- **An antigen-binding domain** outside the cell, typically a single-chain variable fragment (scFv) built from the variable regions of an antibody's heavy and light chains. This is the part that finds the target.
- **A hinge region,** which affects the flexibility of the binding domain and its access to the target.
- **A transmembrane domain,** which anchors the receptor in the cell membrane; most are derived from the proteins CD3ζ, CD4, CD8α or CD28.
- **Intracellular signalling domains,** which activate the T cell when the receptor binds.
- **An antigen-binding domain** outside the cell, typically a single-chain variable fragment (scFv) built from the variable regions of an antibody's heavy and light chains. This is the part that finds the target.
- **A hinge region,** which affects the flexibility of the binding domain and its access to the target.
- **A transmembrane domain,** which anchors the receptor in the cell membrane; most are derived from the proteins CD3ζ, CD4, CD8α or CD28.[2]
- **Intracellular signalling domains,** which activate the T cell when the receptor binds.
The review groups CAR designs into generations by their signalling parts. First-generation CARs, built in the late 1990s, carried only an activating domain derived from CD3ζ or FcRγ, and showed [limited durability and clinical efficacy](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/). Second-generation CARs add one costimulatory domain, a second internal signal that helps the cell persist and multiply; CD28 and 4-1BB are the two used in the FDA-approved products. Third-generation CARs add two costimulatory domains, with mixed results in laboratory models, some of which showed no advantage over second-generation designs.
The review groups CAR designs into generations by their signalling parts. First-generation CARs, built in the late 1990s, carried only an activating domain derived from CD3ζ or FcRγ, and showed [limited durability and clinical efficacy](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/).[2] Second-generation CARs add one costimulatory domain, a second internal signal that helps the cell persist and multiply; CD28 and 4-1BB are the two used in the FDA-approved products.[2] Third-generation CARs add two costimulatory domains, with mixed results in laboratory models, some of which showed no advantage over second-generation designs.
## Origins
## Origins
The idea of giving a T cell antibody-like targeting was published in December 1989, when Gideon Gross, Tova Waks and Zelig Eshhar of the Weizmann Institute of Science reported in the *Proceedings of the National Academy of Sciences* that they had fused the variable domains of an antibody to T-cell receptor constant domains, creating [chimeric molecules that worked as functional receptors with antibody-type specificity](https://pmc.ncbi.nlm.nih.gov/articles/PMC298636/). Cells carrying the chimeric receptor killed target cells bearing the chemical group the antibody recognised, and did so without the usual molecular restriction, across strain and species barriers.
The idea of giving a T cell antibody-like targeting was published in December 1989, when Gideon Gross, Tova Waks and Zelig Eshhar of the Weizmann Institute of Science reported in the *Proceedings of the National Academy of Sciences* that they had fused the variable domains of an antibody to T-cell receptor constant domains, creating [chimeric molecules that worked as functional receptors with antibody-type specificity](https://pmc.ncbi.nlm.nih.gov/articles/PMC298636/).[3] Cells carrying the chimeric receptor killed target cells bearing the chemical group the antibody recognised, and did so without the usual molecular restriction, across strain and species barriers.[3]
Two decades of laboratory work followed before the approach reached patients in a form that worked. The target that made the difference was CD19, a protein on the surface of B cells, the immune cells that make antibodies; the cancers CAR T-cell therapy was first approved for are cancers of those cells, and the Sterners' review notes that clinical success with [anti-CD19 CAR-T cell therapy against B cell malignancies](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) is what led to the FDA's 2017 approval.
Two decades of laboratory work followed before the approach reached patients in a form that worked. The target that made the difference was CD19, a protein on the surface of B cells, the immune cells that make antibodies; the cancers CAR T-cell therapy was first approved for are cancers of those cells, and the Sterners' review notes that clinical success with [anti-CD19 CAR-T cell therapy against B cell malignancies](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) is what led to the FDA's 2017 approval.
## First patients and approval
## First patients and approval
In 2012 a phase 1 trial at the Children's Hospital of Philadelphia (CHOP) gave CD19-directed CAR T cells to children with acute lymphoblastic leukaemia (ALL) for the first time. The hospital's account names the first of them, Emily Whitehead, then [six years old](https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free), whose T cells were harvested in March 2012 and reinfused about a month later after her leukaemia had returned. The cells were engineered in the manufacturing laboratory at the University of Pennsylvania, where the therapy had been developed by [Carl June, Bruce Levine and David Porter](https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free), and the trial was run at CHOP by the paediatric oncologist Stephan Grupp. CHOP reported in May 2022 that she had then been ten years cancer-free and that the hospital had [treated more than 440 patients](https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free) with the therapy.
In 2012 a phase 1 trial at the Children's Hospital of Philadelphia (CHOP) gave CD19-directed CAR T cells to children with acute lymphoblastic leukaemia (ALL) for the first time.[4] The hospital's account names the first of them, Emily Whitehead, then [six years old](https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free), whose T cells were harvested in March 2012 and reinfused about a month later after her leukaemia had returned. The cells were engineered in the manufacturing laboratory at the University of Pennsylvania, where the therapy had been developed by [Carl June, Bruce Levine and David Porter](https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free), and the trial was run at CHOP by the paediatric oncologist Stephan Grupp. CHOP reported in May 2022 that she had then been ten years cancer-free and that the hospital had [treated more than 440 patients](https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free) with the therapy.[4]
NCI records that the FDA approved the first CAR T-cell therapy in 2017: [tisagenlecleucel (Kymriah), for children with ALL](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells), the same product used in the CHOP trial, which CHOP dates to 30 August 2017. Later approvals covered adults with other blood cancers, including non-Hodgkin lymphoma and multiple myeloma.
NCI records that the FDA approved the first CAR T-cell therapy in 2017: [tisagenlecleucel (Kymriah), for children with ALL](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells), the same product used in the CHOP trial, which CHOP dates to 30 August 2017. Later approvals covered adults with other blood cancers, including non-Hodgkin lymphoma and multiple myeloma.[1]
3 unchanged paragraphs
## The approved therapies
## The approved therapies
As of NCI's February 2025 page, the [seven approved products](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells) and their uses were:
As of NCI's February 2025 page, the [seven approved products](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells) and their uses were:
| Product | Approved uses |
|---|---|
| Abecma (ide-cel) | Multiple myeloma |
| Aucatzyl (obe-cel) | B-cell ALL (adult) |
| Breyanzi (liso-cel) | Follicular lymphoma; large B-cell lymphoma; mantle cell lymphoma; chronic lymphocytic leukaemia |
| Carvykti (cilta-cel) | Multiple myeloma |
| Kymriah (tisa-cel) | B-cell ALL (paediatric and young adult); diffuse large B-cell lymphoma; follicular lymphoma |
| Tecartus (brexu-cel) | B-cell ALL (adult); mantle cell lymphoma |
| Yescarta (axi-cel) | Large B-cell lymphoma; follicular lymphoma |
| Product | Approved uses |
|---|---|
| Abecma (ide-cel) | Multiple myeloma |
| Aucatzyl (obe-cel) | B-cell ALL (adult) |
| Breyanzi (liso-cel) | Follicular lymphoma; large B-cell lymphoma; mantle cell lymphoma; chronic lymphocytic leukaemia |
| Carvykti (cilta-cel) | Multiple myeloma |
| Kymriah (tisa-cel) | B-cell ALL (paediatric and young adult); diffuse large B-cell lymphoma; follicular lymphoma |
| Tecartus (brexu-cel) | B-cell ALL (adult); mantle cell lymphoma |
| Yescarta (axi-cel) | Large B-cell lymphoma; follicular lymphoma |
The FDA describes the approved autologous products as either CD19-directed or [BCMA-directed](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed) (BCMA stands for B-cell maturation antigen). NCI says the 2017 approval of tisagenlecleucel rested on trials showing it [eliminated leukemia in most children with relapsed ALL](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells).
The FDA describes the approved autologous products as either CD19-directed or [BCMA-directed](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed) (BCMA stands for B-cell maturation antigen).[5] NCI says the 2017 approval of tisagenlecleucel rested on trials showing it [eliminated leukemia in most children with relapsed ALL](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells).[1]
## Manufacture and infusion
## Manufacture and infusion
NCI sets out four steps: blood is collected from the patient and the T cells separated out; in a manufacturer's laboratory they are genetically engineered to produce CARs; the modified cells are multiplied until there are [hundreds of millions of them](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells); and they are returned to the hospital and given as a single infusion. The whole process takes [about 3 to 5 weeks](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells). Because every dose is grown from one patient's own cells, these are autologous therapies: a drug manufactured once, for one person.
NCI sets out four steps: blood is collected from the patient and the T cells separated out; in a manufacturer's laboratory they are genetically engineered to produce CARs; the modified cells are multiplied until there are [hundreds of millions of them](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells); and they are returned to the hospital and given as a single infusion.[1] The whole process takes [about 3 to 5 weeks](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells).[1] Because every dose is grown from one patient's own cells, these are autologous therapies: a drug manufactured once, for one person.
4 unchanged paragraphs
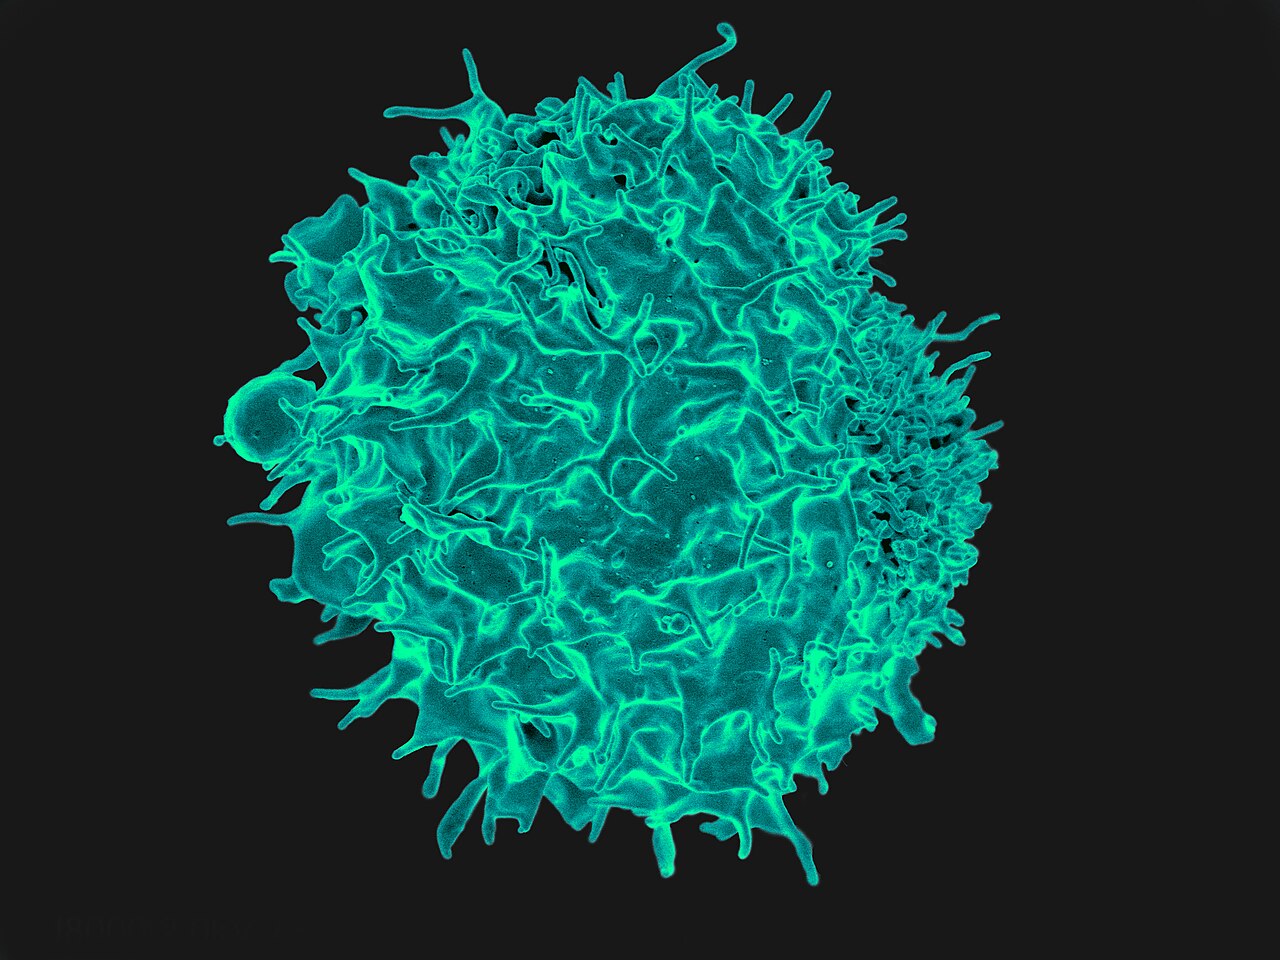

*Via Wikimedia Commons: [T Lymphocyte (16760076824)](https://commons.wikimedia.org/wiki/File:T_Lymphocyte_(16760076824).jpg) by NIAID, [CC BY 2.0](https://creativecommons.org/licenses/by/2.0).*
*Via Wikimedia Commons: [T Lymphocyte (16760076824)](https://commons.wikimedia.org/wiki/File:T_Lymphocyte_(16760076824).jpg) by NIAID, [CC BY 2.0](https://creativecommons.org/licenses/by/2.0).*
## Side effects
## Side effects
Two reactions dominate the safety record, and both follow from the therapy working.
Two reactions dominate the safety record, and both follow from the therapy working.
**Cytokine release syndrome (CRS)** occurs when, as NCI puts it, [the infused T cells flood the bloodstream with cytokines](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells), the signalling molecules immune cells use to call in reinforcements. The result can include very high fevers and sharp falls in blood pressure. NCI reports that it is often managed with the antibody tocilizumab, which blocks one cytokine's receptor, and with steroids if needed. The Sterners' review reports CRS in [77–93% of patients with leukaemia](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) treated with CAR T cells, with 46 percent of patients given tisagenlecleucel for B-ALL having grade 3 or higher CRS.
**Cytokine release syndrome (CRS)** occurs when, as NCI puts it, [the infused T cells flood the bloodstream with cytokines](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells), the signalling molecules immune cells use to call in reinforcements.[1] The result can include very high fevers and sharp falls in blood pressure. NCI reports that it is often managed with the antibody tocilizumab, which blocks one cytokine's receptor, and with steroids if needed.[1] The Sterners' review reports CRS in [77–93% of patients with leukaemia](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) treated with CAR T cells, with 46 percent of patients given tisagenlecleucel for B-ALL having grade 3 or higher CRS.[2]
**Neurological effects,** known as immune effector cell-associated neurotoxicity syndrome (ICANS), include confusion, excessive sleepiness and impaired speech, according to NCI, which notes that steroids are the usual treatment and that the drug anakinra may help when steroids do not. The review reports neurotoxicity in up to [67% of leukaemia patients and 62% of lymphoma patients](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) in the trials it surveys.
**Neurological effects,** known as immune effector cell-associated neurotoxicity syndrome (ICANS), include confusion, excessive sleepiness and impaired speech, according to NCI, which notes that steroids are the usual treatment and that the drug anakinra may help when steroids do not.[1] The review reports neurotoxicity in up to [67% of leukaemia patients and 62% of lymphoma patients](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) in the trials it surveys.[2]
In November 2023 the FDA began investigating reports of T-cell cancers in people who had received these therapies. On 18 April 2024 it concluded that [changes to the Boxed Warning are warranted to highlight the serious risk of T cell malignancies](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed), finding that the risk applied to all approved BCMA- and CD19-directed autologous CAR T products: Abecma, Breyanzi, Carvykti, Kymriah, Tecartus and Yescarta. The agency stated that such cancers [may present as soon as weeks following infusion, and may include fatal outcomes](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed), and said patients should be monitored life-long.
In November 2023 the FDA began investigating reports of T-cell cancers in people who had received these therapies. On 18 April 2024 it concluded that [changes to the Boxed Warning are warranted to highlight the serious risk of T cell malignancies](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed), finding that the risk applied to all approved BCMA- and CD19-directed autologous CAR T products: Abecma, Breyanzi, Carvykti, Kymriah, Tecartus and Yescarta.[5] The agency stated that such cancers [may present as soon as weeks following infusion, and may include fatal outcomes](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed), and said patients should be monitored life-long.[5]
## Regulation of how it is given
## Regulation of how it is given
Because of CRS and neurological toxicity, the FDA originally required a Risk Evaluation and Mitigation Strategy (REMS) for these products: hospitals had to be specially certified and keep tocilizumab on site. On 26 June 2025 the agency eliminated the REMS for all six then-approved BCMA- and CD19-directed autologous products, having determined that [a REMS is no longer necessary to ensure that the benefits of the above CAR T cell immunotherapies outweigh their risks](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-eliminates-risk-evaluation-and-mitigation-strategies-rems-autologous-chimeric-antigen-receptor), citing clinicians' experience in managing the toxicities, stable adverse-event reporting, and the burden of compliance on the health system; it expected the change to improve access, particularly for patients in rural areas. The labels were revised at the same time to require that patients be monitored [for at least two weeks including daily monitoring for at least one week](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-eliminates-risk-evaluation-and-mitigation-strategies-rems-autologous-chimeric-antigen-receptor), stay near a healthcare facility for two weeks and avoid driving for the same period, in place of the longer restrictions the REMS had imposed. Routine adverse-event reporting continues, and manufacturers must still follow patients for 15 years after treatment to assess secondary cancers and long-term safety.
Because of CRS and neurological toxicity, the FDA originally required a Risk Evaluation and Mitigation Strategy (REMS) for these products: hospitals had to be specially certified and keep tocilizumab on site.[6] On 26 June 2025 the agency eliminated the REMS for all six then-approved BCMA- and CD19-directed autologous products, having determined that [a REMS is no longer necessary to ensure that the benefits of the above CAR T cell immunotherapies outweigh their risks](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-eliminates-risk-evaluation-and-mitigation-strategies-rems-autologous-chimeric-antigen-receptor), citing clinicians' experience in managing the toxicities, stable adverse-event reporting, and the burden of compliance on the health system; it expected the change to improve access, particularly for patients in rural areas.[6] The labels were revised at the same time to require that patients be monitored [for at least two weeks including daily monitoring for at least one week](https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-eliminates-risk-evaluation-and-mitigation-strategies-rems-autologous-chimeric-antigen-receptor), stay near a healthcare facility for two weeks and avoid driving for the same period, in place of the longer restrictions the REMS had imposed. Routine adverse-event reporting continues, and manufacturers must still follow patients for 15 years after treatment to assess secondary cancers and long-term safety.
## Limits in solid tumours
## Limits in solid tumours
Every approved CAR T-cell therapy treats a blood cancer. NCI gives three reasons the approach has been hard to extend to solid tumours such as those of the breast, lung or brain: researchers have struggled to find antigens that appear on solid tumour cells but not on healthy tissue; the [immunosuppressive environment](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells) in and around a tumour can stop CAR T cells reaching it or make them malfunction; and tumours of the same type differ greatly between patients and even within one patient, a problem NCI calls "age-old".
Every approved CAR T-cell therapy treats a blood cancer.[1] NCI gives three reasons the approach has been hard to extend to solid tumours such as those of the breast, lung or brain: researchers have struggled to find antigens that appear on solid tumour cells but not on healthy tissue; the [immunosuppressive environment](https://www.cancer.gov/about-cancer/treatment/research/car-t-cells) in and around a tumour can stop CAR T cells reaching it or make them malfunction; and tumours of the same type differ greatly between patients and even within one patient, a problem NCI calls "age-old".[1]
The Sterners' review adds that [physical tumour barriers such as the tumour stroma limit the penetration and mobility of CAR-T cells](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/), and surveys attempted answers, including delivering the cells directly to the site rather than into a vein, and engineering them to carry receptors that help them follow chemical trails into tissue.
The Sterners' review adds that [physical tumour barriers such as the tumour stroma limit the penetration and mobility of CAR-T cells](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/), and surveys attempted answers, including delivering the cells directly to the site rather than into a vein, and engineering them to carry receptors that help them follow chemical trails into tissue.[2]
A separate limit applies in blood cancers too. The review reports that 70–90 percent of patients with relapsed or refractory ALL respond durably to CD19 CAR T-cell therapy, but that in those whose disease comes back, [downregulation/loss of CD19 antigen in 30–70% of patients](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) has been reported: the cancer survives by ceasing to display the protein the CAR was built to find. Designs that aim at two targets at once, such as CD19 together with CD22 or BCMA, are being tested against this kind of escape.
A separate limit applies in blood cancers too. The review reports that 70–90 percent of patients with relapsed or refractory ALL respond durably to CD19 CAR T-cell therapy, but that in those whose disease comes back, [downregulation/loss of CD19 antigen in 30–70% of patients](https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/) has been reported: the cancer survives by ceasing to display the protein the CAR was built to find.[2] Designs that aim at two targets at once, such as CD19 together with CD22 or BCMA, are being tested against this kind of escape.[2]
## Use in autoimmune disease
## Use in autoimmune disease
Because CD19 marks B cells rather than cancer as such, the same therapy can be used to clear B cells in diseases where they drive an attack on the patient's own tissues. In February 2024 Fabian Müller, Georg Schett and colleagues at Friedrich-Alexander-Universität Erlangen-Nürnberg reported in the *New England Journal of Medicine* on [fifteen patients](https://pubmed.ncbi.nlm.nih.gov/38381673/) with severe autoimmune disease: eight with systemic lupus erythematosus, three with idiopathic inflammatory myositis and four with systemic sclerosis, each given a single infusion of CD19 CAR T cells after preconditioning chemotherapy. Over a median follow-up of 15 months, all the lupus patients reached remission by the DORIS definition, all the myositis patients had a major clinical response by ACR-EULAR criteria, and all the systemic sclerosis patients had lower disease-activity scores; immunosuppressive drugs were stopped in every patient. B cells disappeared for a mean of 112 days and then returned. Side effects were milder than in cancer use: grade 1 CRS in ten patients, one case of grade 2 CRS, one of grade 1 neurotoxicity and one pneumonia requiring hospital admission. The authors described the approach as [feasible, safe, and efficacious in three different autoimmune diseases](https://pubmed.ncbi.nlm.nih.gov/38381673/) and called for controlled clinical trials; the series was uncontrolled and small, with patients of three different diseases treated at one centre.
Because CD19 marks B cells rather than cancer as such, the same therapy can be used to clear B cells in diseases where they drive an attack on the patient's own tissues. In February 2024 Fabian Müller, Georg Schett and colleagues at Friedrich-Alexander-Universität Erlangen-Nürnberg reported in the *New England Journal of Medicine* on [fifteen patients](https://pubmed.ncbi.nlm.nih.gov/38381673/) with severe autoimmune disease: eight with systemic lupus erythematosus, three with idiopathic inflammatory myositis and four with systemic sclerosis, each given a single infusion of CD19 CAR T cells after preconditioning chemotherapy.[7] Over a median follow-up of 15 months, all the lupus patients reached remission by the DORIS definition, all the myositis patients had a major clinical response by ACR-EULAR criteria, and all the systemic sclerosis patients had lower disease-activity scores; immunosuppressive drugs were stopped in every patient.[7] B cells disappeared for a mean of 112 days and then returned. Side effects were milder than in cancer use: grade 1 CRS in ten patients, one case of grade 2 CRS, one of grade 1 neurotoxicity and one pneumonia requiring hospital admission. The authors described the approach as [feasible, safe, and efficacious in three different autoimmune diseases](https://pubmed.ncbi.nlm.nih.gov/38381673/) and called for controlled clinical trials; the series was uncontrolled and small, with patients of three different diseases treated at one centre.[7]
3 unchanged paragraphs
This entry explains; it is not medical advice. Ask a doctor or pharmacist about your own health.
This entry explains; it is not medical advice. Ask a doctor or pharmacist about your own health.
## Sources
## Sources
- National Cancer Institute, "CAR T Cells: Engineering Immune Cells to Treat Cancer", updated 26 February 2025. https://www.cancer.gov/about-cancer/treatment/research/car-t-cells
- Robert C. Sterner and Rosalie M. Sterner, "CAR-T cell therapy: current limitations and potential strategies", *Blood Cancer Journal* 11(69), 6 April 2021. https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/
- G. Gross, T. Waks and Z. Eshhar, "Expression of immunoglobulin-T-cell receptor chimeric molecules as functional receptors with antibody-type specificity", *Proceedings of the National Academy of Sciences* 86(24), December 1989, pp. 10024–10028. https://pmc.ncbi.nlm.nih.gov/articles/PMC298636/
- Children's Hospital of Philadelphia, "First Child to Receive Revolutionary CAR T Therapy Celebrates 10 Years Cancer Free", 10 May 2022. https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free
- U.S. Food and Drug Administration, "FDA Requires Boxed Warning for T cell Malignancies Following Treatment with BCMA-Directed or CD19-Directed Autologous Chimeric Antigen Receptor (CAR) T cell Immunotherapies", 18 April 2024. https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed
- U.S. Food and Drug Administration, "FDA Eliminates Risk Evaluation and Mitigation Strategies (REMS) for Autologous Chimeric Antigen Receptor (CAR) T cell Immunotherapies", 26 June 2025. https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-eliminates-risk-evaluation-and-mitigation-strategies-rems-autologous-chimeric-antigen-receptor
- Fabian Müller, Jule Taubmann, Laura Bucci and others, "CD19 CAR T-Cell Therapy in Autoimmune Disease — A Case Series with Follow-up", *New England Journal of Medicine* 390(8), 22 February 2024, pp. 687–700, doi:10.1056/NEJMoa2308917 (record and abstract read via PubMed and Europe PMC). https://pubmed.ncbi.nlm.nih.gov/38381673/
- National Cancer Institute, "CAR T Cells: Engineering Immune Cells to Treat Cancer", updated 26 February 2025. https://www.cancer.gov/about-cancer/treatment/research/car-t-cells
- Robert C. Sterner and Rosalie M. Sterner, "CAR-T cell therapy: current limitations and potential strategies", *Blood Cancer Journal* 11(69), 6 April 2021. https://pmc.ncbi.nlm.nih.gov/articles/PMC8024391/
- G. Gross, T. Waks and Z. Eshhar, "Expression of immunoglobulin-T-cell receptor chimeric molecules as functional receptors with antibody-type specificity", *Proceedings of the National Academy of Sciences* 86(24), December 1989, pp. 10024–10028. https://pmc.ncbi.nlm.nih.gov/articles/PMC298636/
- Children's Hospital of Philadelphia, "First Child to Receive Revolutionary CAR T Therapy Celebrates 10 Years Cancer Free", 10 May 2022. https://www.chop.edu/news/first-child-receive-revolutionary-car-t-therapy-celebrates-10-years-cancer-free
- U.S. Food and Drug Administration, "FDA Requires Boxed Warning for T cell Malignancies Following Treatment with BCMA-Directed or CD19-Directed Autologous Chimeric Antigen Receptor (CAR) T cell Immunotherapies", 18 April 2024. https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-requires-boxed-warning-t-cell-malignancies-following-treatment-bcma-directed-or-cd19-directed
- U.S. Food and Drug Administration, "FDA Eliminates Risk Evaluation and Mitigation Strategies (REMS) for Autologous Chimeric Antigen Receptor (CAR) T cell Immunotherapies", 26 June 2025. https://www.fda.gov/vaccines-blood-biologics/safety-availability-biologics/fda-eliminates-risk-evaluation-and-mitigation-strategies-rems-autologous-chimeric-antigen-receptor
- Fabian Müller, Jule Taubmann, Laura Bucci and others, "CD19 CAR T-Cell Therapy in Autoimmune Disease — A Case Series with Follow-up", *New England Journal of Medicine* 390(8), 22 February 2024, pp. 687–700, doi:10.1056/NEJMoa2308917 (record and abstract read via PubMed and Europe PMC). https://pubmed.ncbi.nlm.nih.gov/38381673/
