Version 4 (current)
Nov 16, 2026. Version history
Osteoporosis is a disease of the skeleton in which bones lose strength, becoming weak and fragile, so that they break more easily, often after only a minor fall or injury.
Definition
The most widely cited definition comes from a consensus conference held by the U.S. National Institutes of Health in March 2000.[2][5] It describes osteoporosis as a "skeletal disorder characterized by compromised bone strength predisposing a person to an increased risk of fracture", with bone strength said to reflect "the integration of bone density and bone quality". The panel's statement, published in JAMA in February 2001, noted that although the disease is common in white postmenopausal women, it "occurs in all populations and at all ages".[2]
In practice, osteoporosis is usually identified by measuring bone mineral density (BMD), the amount of mineral in a given area of bone. The diagnostic categories in use today were set out by a World Health Organization study group that met in Rome in June 1992 and reported in 1994 (WHO Technical Report Series 843). The report defined four categories for women, measured against the average for healthy young adults:
- Normal: bone mineral within 1 standard deviation of the young adult mean.
- Low bone mass (osteopenia): between 1 and 2.5 standard deviations below that mean.
- Osteoporosis: 2.5 standard deviations or more below it.
- Severe (established) osteoporosis: more than 2.5 standard deviations below it, together with one or more fragility fractures.
A standard deviation is a measure of how widely values in a population are spread around their average. The study group acknowledged that "all cut-off values are somewhat arbitrary", and that people are classified differently depending on the site measured, the technique and the reference population used. It also drew a distinction between diagnosing the disease and predicting fractures: low bone density, it argued, is a risk factor for fracture in the way that high blood pressure is a risk factor for stroke (see Hypertension), and a person with osteoporosis will not invariably break a bone, while a person judged at low risk from a bone density measurement may still have a fragility fracture.
History
Fragile bones in old age were noticed long before the disease had its present name. In the early nineteenth century the English surgeon Sir Astley Cooper wrote of the "lightness and softness" that bones acquire "in the more advanced stages of life", as recounted in a 2005 review by Lawrence Raisz, and a 2023 historical review by Francesco Galassi and Elena Varotto credits Cooper with first linking a structural abnormality of bone to later fractures.[7][8] The same review dates the term "osteoporosis" (French ostéoporose) to 1833, in the second volume of Johann Lobstein's Traité d'anatomie pathologique, where he described an expansion of the marrow spaces at the expense of trabecular (spongy) bone.[8] Both reviews suggest that what Lobstein described was probably osteogenesis imperfecta, an inherited disorder of brittle bones, rather than osteoporosis in the modern sense.[7][8]
The modern study of the disease begins with the physician Fuller Albright (1900–1969). A 1940 paper by Albright and colleagues gave the condition the name "menopausal osteoporosis" and reported estrogen treatment in three patients, according to a 2011 biographical sketch in Clinical Orthopaedics and Related Research.[9] In 1941 Albright, Smith and Richardson described 42 cases in JAMA and concluded that the disease was caused by "deficient osteoblastic activity", that is, a failure of bone formation.[8] Later research reversed that part of his account: Raisz wrote in 2005 that, "contrary to Albright's original hypothesis, an increase in bone resorption, and not impaired bone formation, appears to be the driving force for bone loss" when estrogen is lacking.[7]
For a time osteoporosis was thought to take two forms, one related to estrogen deficiency at the menopause and the other to calcium deficiency and the ageing of the skeleton. Raisz describes this view as replaced by the concept that osteoporosis "represents a continuum", in which several mechanisms converge to reduce bone mass and damage the fine structure of bone.[7]
How bone is lost
Bone is living tissue that is continually broken down and rebuilt. A 2020 review in the EXCLI Journal describes this cycle, called remodeling, as a coordinated process in which bone-resorbing cells (osteoclasts) remove old or damaged bone and bone-forming cells (osteoblasts) replace it, directed by osteocytes, former osteoblasts that have become embedded in the bone.[5] In healthy adults the two processes are balanced. At the cellular level, the review explains, osteoporosis results from bone resorption that bone formation does not compensate for.[5]
Much of the modern understanding of this balance rests on the discovery of a signalling system known as RANK, its ligand RANKL and the decoy receptor osteoprotegerin. The review describes RANKL as a master regulator of the formation, activation and survival of osteoclasts.[5] Bone formation, in turn, is driven by the Wnt signalling pathway, which is held in check by a protein called sclerostin; people with rare genetic conditions that leave them without sclerostin have unusually high bone mass.[5]
The loss of estrogen at menopause has been recognised as a key cause of accelerated bone loss since work published by Albright and colleagues in 1941.[5] According to the same review, estrogen loss increases the number of osteoclasts and decreases the number of osteoblasts, tilting remodeling toward resorption.[5] Older explanations of the disease emphasised hormonal factors such as estrogen and vitamin D deficiency; research over the past few decades has added other mechanisms, including interactions between bone and the immune system, the gut microbiome and the ageing of cells.[5] The review calls osteoporosis a classic example of a multifactorial disease, shaped by genetic, internal, environmental and lifestyle factors.[5] Much of this research, particularly on the immune system's role, is still developing.
Risk factors
The UK's National Health Service lists factors that raise the chance of having osteoporosis, among them [older age, the menopause, a parent with osteoporosis, a white ethnic background, not having enough calcium or vitamin D, being underweight, smoking, drinking too much alcohol, little exercise, some health conditions such as diabetes or rheumatoid arthritis, and taking steroid tablets](nhs.uk/conditions/osteoporosis/).[4] The NIH consensus panel noted that the risks for low bone density and for fracture overlap but are not identical, and called for more attention to skeletal health in people with conditions associated with secondary osteoporosis, meaning bone loss that results from another condition.[2] The panel also described calcium and vitamin D intake as crucial to developing optimal peak bone mass (the greatest bone mass a person reaches) and named gonadal steroids (sex hormones) as important determinants of peak and lifetime bone mass in men, women and children.[2]
Symptoms and fractures
Bone loss itself usually causes no symptoms. The WHO study group noted that there is no evidence that postmenopausal bone loss causes any symptoms, which is why it has been called "the silent epidemic" or "silent thief." The NHS likewise states that often the first symptom is breaking a bone after a minor fall or injury, and that small breaks in the bones of the spine can cause back pain, a curved or hunched posture, or loss of height.[4]
The WHO report notes that most osteoporotic fractures occur in the spine, wrist and hip, and that they occur mostly in older women, with incidence rising markedly with age. The NIH consensus statement identified vertebral, rib, hip and distal forearm (wrist) fractures as ones that should prompt an evaluation for osteoporosis.[2] An analysis of Global Burden of Disease data published in 2022 cites estimates that about one in three women and one in five men, typically aged 50 and over, will have a fragility fracture in the rest of their lives, and that adults who have had one type of fracture are 50% to 100% more likely to have a fracture of a different type.[6]
The burden of these fractures is large. Citing Medicare data, the U.S. Preventive Services Task Force reported in January 2025 that approximately 1.8 million beneficiaries had a new osteoporotic fracture in 2016, and that only 40% to 60% of people who have a hip fracture recover their previous level of mobility.[13] It lists psychological distress, further fractures and loss of independence among the consequences of osteoporotic fractures.[13]
Diagnosis
Bone mineral density is measured with dual-energy X-ray absorptiometry (DXA, also written DEXA), an X-ray technique. The NHS describes the bone density scan (DEXA scan) as the test used to check how strong bones are.[4] The U.S. National Center for Health Statistics, in its survey work, measures BMD at the femur neck (the top of the thigh bone) and the lumbar spine and compares it with the mean for young adult women, using the same 1-to-2.5 standard deviation thresholds as the WHO categories.[3] Clinical literature commonly reports such results as a "T-score"; the 2020 review cited below, for example, describes trial participants with T-scores between −2.5 and −3.5.[5]
Bone density is not the only way fracture risk is estimated. FRAX, a calculator launched in 2008 by a team at the University of Sheffield led by Professors Kanis and McCloskey, estimates a person's 10-year probability of a hip fracture and of a major osteoporotic fracture (hip, spine, forearm or shoulder), and can do so without a bone density measurement. The university reports that its models were built on data from about 60,000 people, were validated in an international cohort of about 230,000, are available in 53 countries and 28 languages, and have been incorporated into numerous national and international guidelines.[11] The team worked at a WHO Collaborating Centre in Sheffield, a designation the unit held from 1991 to 2010, but the World Health Organization stated in its Bulletin in December 2016 that FRAX has not been "developed, endorsed, evaluated or validated by WHO".
Who should be tested is a matter for national guidance. In the United States, the Preventive Services Task Force stated on 14 January 2025 that it recommends screening for osteoporosis in women aged 65 or older, and in postmenopausal women under 65 at increased risk of fracture as estimated by clinical risk assessment, both at its grade B, and that the evidence was insufficient to assess the balance of benefits and harms of screening men (grade I).[13] For women of 65 and over it names DXA bone density measurement, with or without fracture risk assessment, as the screening test.
How common it is
In the United States, the National Center for Health Statistics reported in March 2021 that, among adults aged 50 and over in 2017–2018, the age-adjusted prevalence of osteoporosis was 12.6%: 19.6% among women and 4.4% among men.[3] A further 43.1% had low bone mass.[3] Among women, osteoporosis was more common at 65 and over (27.1%) than at 50 to 64 (13.1%).[3] Over the decade from 2007–2008, prevalence rose among women, from 14.0% to 19.6%, but not significantly among men.[3] The figures come from the National Health and Nutrition Examination Survey, in which bone density was measured directly by DXA.
Worldwide, the 2022 analysis of the Global Burden of Disease Study 2019 estimated that deaths attributable to low bone mineral density rose from 207,367 in 1990 to 437,884 in 2019, and disability-adjusted life-years (a measure of years of healthy life lost) from about 8.6 million to 16.6 million.[6] Because death records attribute such deaths to causes like falls rather than to fractures, the study estimated the burden by linking low bone density to injuries known to cause fractures. In 2019 the countries with the largest burden of fractures related to low bone density, measured in disability-adjusted life-years, were India, China, the United States, Japan and Germany.[6] The authors expect the ageing of the world's population and changing lifestyles to raise rates of chronic diseases such as osteoporosis.[6]
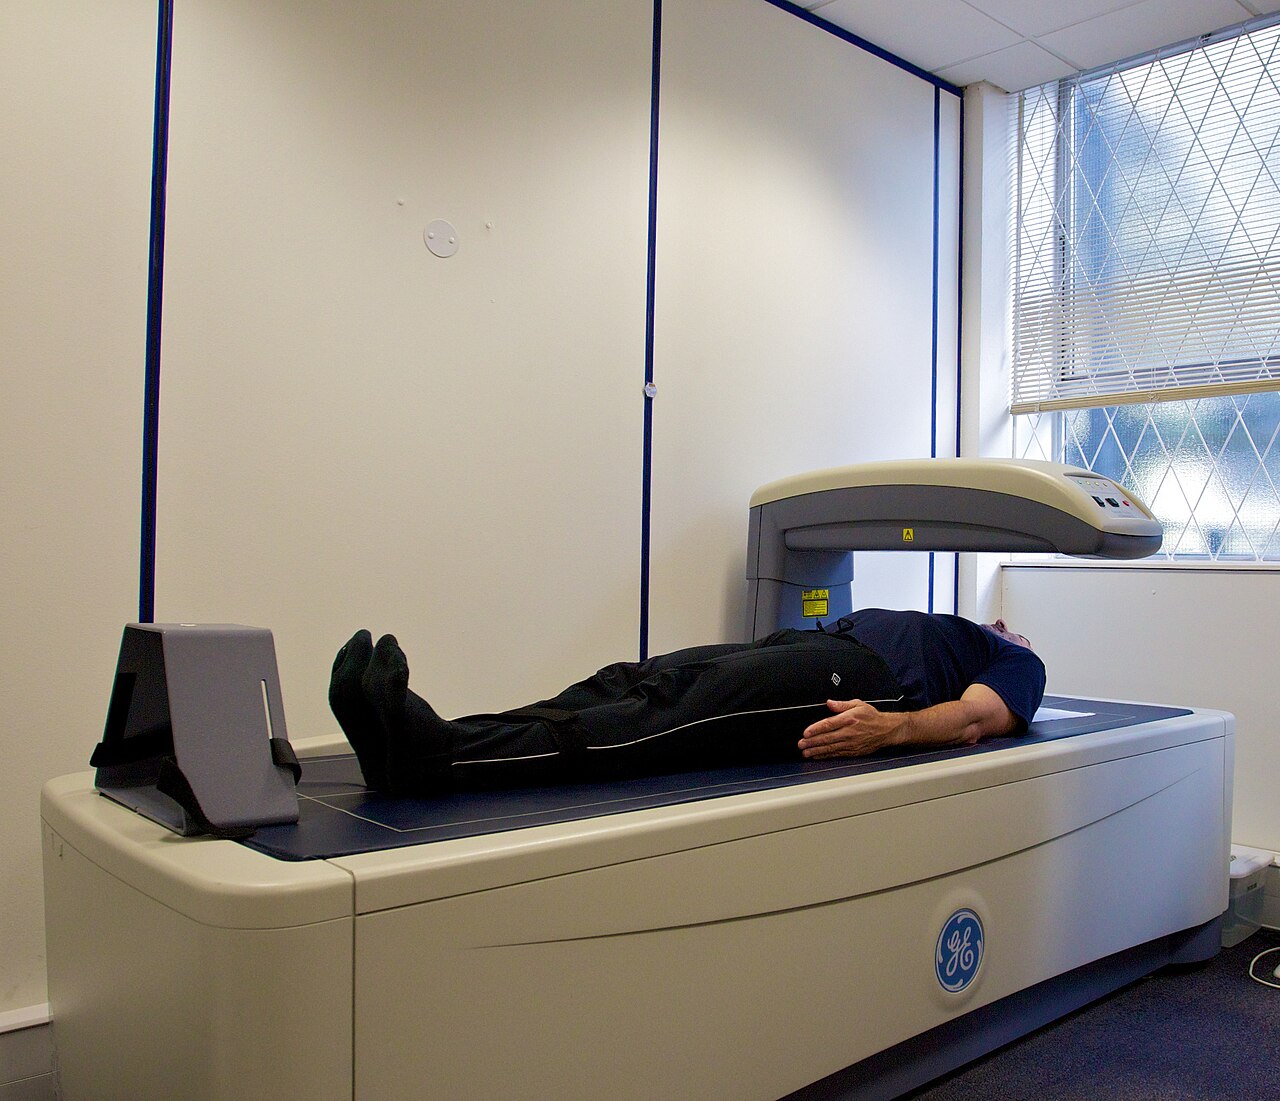
Via Wikimedia Commons: DEXA scanner in use ALSPAC by Nick Smith photography, CC BY-SA 3.0.
Medicines and research
Drug treatment for the disease goes back to Albright. A 2017 review in The Lancet Diabetes & Endocrinology by Sundeep Khosla and Lorenz Hofbauer credits his 1940s work with showing that estrogen could reverse the negative calcium balance that develops in women after the menopause or removal of the ovaries.[10] The discovery of bisphosphonates as effective osteoporosis drugs was, in the authors' words, "largely opportunistic", and how they act on osteoclasts was worked out decades after they entered clinical use. The review identifies a watershed around the year 2000, after which new drugs came from advances in basic bone biology: denosumab from the discovery of RANKL, and romosozumab from the study of sclerosteosis and van Buchem disease, two rare inherited bone disorders that served as so-called "experiments of nature" showing what blocking sclerostin could do.[10] The same review warned of "an increasing treatment gap" for patients at high risk of fracture.[10]
Several classes of medicine have been developed for osteoporosis. The NHS divides them into medicines that stop or slow down damage to bones (bisphosphonates) and medicines that speed up the building of new bone (anabolic agents).[4] The NIH consensus panel stated that fracture prevention is the primary treatment goal and that several treatments, including those that increase bone mass and those that reduce the risk or consequences of falls, had been shown to reduce fracture risk.[2]
The 2020 EXCLI Journal review describes the main groups as follows:
- Bisphosphonates attach to the mineral surface of bone where it is being resorbed and inhibit osteoclasts.[5] Rare side effects reported with them include osteonecrosis (death of bone tissue) of the jaw and atypical fractures of the thigh bone.
- Denosumab is a monoclonal antibody that blocks RANKL, the signal osteoclasts need.[5] The review notes an increased rate of spinal fractures after it is stopped.
- Selective estrogen receptor modulators (SERMs), such as raloxifene, are synthetic compounds that act on estrogen receptors; the review reports that raloxifene reduced vertebral fractures but did not protect against hip fractures in trials.[5]
- Hormone replacement therapy reduces bone resorption, but the review notes that in the Women's Health Initiative studies it increased the risk of breast cancer, stroke and blood clots in older women, and that it is not regarded as a first-line osteoporosis treatment.[5]
- Bone-forming (osteoanabolic) drugs act on osteoblasts.[5] Teriparatide and abaloparatide are versions of parathyroid hormone; romosozumab is an antibody against sclerostin. The review reports that teriparatide and romosozumab were more effective in reducing vertebral and non-vertebral fractures than antiresorptive drugs.
Which medicine is used, and when, is decided case by case: the review states that the choice is a matter of clinical judgement considering side effects, effects on different parts of the skeleton, and costs.[5] Research continues on new targets, including the immune mechanisms and cellular ageing described above.
This entry explains; it is not medical advice. Ask a doctor or pharmacist about your own health.
Sources
- World Health Organization, Assessment of fracture risk and its application to screening for postmenopausal osteoporosis: report of a WHO Study Group (meeting held in Rome, 22–25 June 1992), WHO Technical Report Series 843, 1994. iris.who.int/handle/10665/39142
- NIH Consensus Development Panel on Osteoporosis Prevention, Diagnosis, and Therapy, "Osteoporosis prevention, diagnosis, and therapy", JAMA 285(6):785–795, 14 February 2001 (PubMed abstract). pubmed.ncbi.nlm.nih.gov/11176917/
- Neda Sarafrazi, Edwina A. Wambogo and John A. Shepherd, "Osteoporosis or Low Bone Mass in Older Adults: United States, 2017–2018", NCHS Data Brief No. 405, National Center for Health Statistics, Centers for Disease Control and Prevention, March 2021. cdc.gov/nchs/products/databriefs/db405.htm
- National Health Service (UK), "Osteoporosis", last reviewed 29 October 2026. nhs.uk/conditions/osteoporosis/
- Ursula Föger-Samwald, Peter Dovjak, Ursula Azizi-Semrad, Katharina Kerschan-Sch
